What the Anion Gap Indicates
The anion gap is a useful way to assess the balance between measured cations and measured anions in the blood. It is commonly included as part of a serum chemistry or an electrolyte panel to help detect an electrolyte imbalance and guide clinical interpretation of acid-base disorders. In simple terms, the calculation examines serum sodium against serum chloride and bicarbonate to suggest whether unmeasured acids may be present.
An anion gap calculator is a useful diagnostic tool because it helps translate raw laboratory values into an actionable calculated value. That value can indicate a hidden metabolic derangement, especially when a patient is in an acidotic state. The result does not stand alone; instead, it adds to an interpretation framework that includes symptoms, laboratory context, and blood gas findings.
The core idea behind the anion gap is that plasma must remain electrically neutral. If sodium is higher than what chloride and bicarbonate account for, the remaining difference reflects unmeasured ions such as lactate, ketones, or retained acids. This is why the anion gap is so valuable for recognizing hidden acidosis and other disturbances that may not be obvious from pH alone.
How to Use an Anion Gap Calculator
An anion gap calculator usually needs the patient’s serum sodium, serum chloride, bicarbonate, and sometimes serum albumin. Most calculators can also use albumin correction to deliver a more accurate corrected anion gap. Because albumin is a major unmeasured anion, low albumin can lead the gap to seem deceptively normal.
The standard calculation formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Using this formula, the calculator returns a calculated value that can be compared with the normal reference interval. If the value is elevated, that points to anion gap elevation and may indicate high-gap metabolic processes. If the value is normal but acidosis is present, a different pattern may be present, such as hyperchloremic acidosis.
When using the calculator, input the same chemistry values used in the lab report. If serum albumin is available, apply albumin correction so the result reflects the true acid-base picture. This matters especially in critically ill patients, where low albumin can mask a significant acid load.
A practical practical approach is to check the anion gap after reviewing the serum chemistry, then compare it with blood gas results. This gives a more complete clinical interpretation than either test alone. In other words, the calculator is most useful when it is part of a broader bedside assessment rather than a standalone number.
Blood Gas Analysis and Acid-Base Interpretation
Blood gas testing supplies essential insight to the anion gap by showing the patient’s pH, carbon dioxide partial pressure, and bicarbonate balance. An arterial blood gas is often used to assess oxygenation and ventilation as well as acid-base control, while a venous blood gas can still be helpful for pH and carbon dioxide patterns in many clinical settings. These tests can support interpretation, but they should be read with awareness of their distinct features.
The pH tells you whether the patient is acidemic or alkalemic. The carbon dioxide partial pressure helps determine whether the primary process is respiratory or metabolic, and bicarbonate indicates the metabolic component. If the pH is low and bicarbonate is low, the pattern often points toward metabolic acidosis. If carbon dioxide is also low, that may indicate respiratory compensation as the body attempts to offset the acid load.
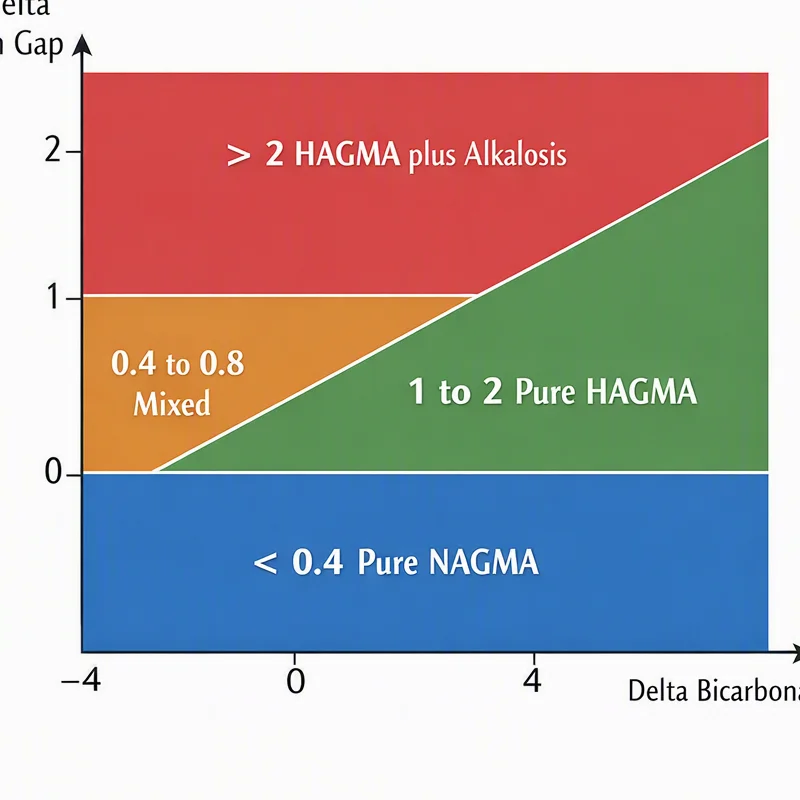
Blood gas analysis becomes especially valuable when paired with the anion gap. A low pH with low bicarbonate and elevated anion gap strongly suggests a high-gap acid load. A low pH with low bicarbonate but normal anion gap may instead suggest bicarbonate loss. This combination of findings allows a more precise acid-base diagnosis and avoids overreliance on a single calculated number.
It is also necessary to consider whether the blood gas is showing a primary metabolic problem, a primary respiratory problem, or a mixed disorder. The pH provides the overall direction, while the carbon dioxide partial pressure helps determine whether the lungs are compensating appropriately. That relationship is fundamental to meaningful clinical interpretation.
Rules, Expected Values, and Corrections
The standard anion gap formula is simple, but the meaning is more nuanced. Most labs base it on sodium minus chloride and bicarbonate, though some also add potassium. Because potassium is usually a limited contributor, many clinicians prefer the basic version. What matters most is consistency and knowing which reference interval matches to the lab method being used.
The reference range for the anion gap varies by laboratory analyzer and local reporting standards. A common normal anion gap is frequently in the low to mid teens, but the exact range depends on the assay and whether potassium is included. That is why the number should always be interpreted in the context of the lab’s own reference interval rather than an assumed universal cutoff.
Albumin correction is important when serum albumin is low. Because albumin is a major unmeasured anion, hypoalbuminemia lowers the expected anion gap. Without correction, a patient may appear to have a normal value even though a significant acid burden is present. The result is a better adjusted corrected anion gap, which is particularly useful in patients with chronic illness, inflammation, or fluid shifts.
The key practical lesson is that the anion gap should not be interpreted in isolation. The number is best viewed in combination with bicarbonate, pH, and carbon dioxide as part of a broader acid-base assessment. That integrated approach enhances confidence and reduces the risk of missing a clinically important metabolic disorder.
Elevated Anion Gap Acid-Base Acidosis
High anion gap metabolic acidosis occurs when unmeasured acids build up in the bloodstream. This is considered one of the most important patterns detected by the anion gap because it can identify severe disease early. In many cases, the anion gap is raised before the complete clinical picture becomes obvious, making it a useful indicator of developing metabolic acidosis.
Common causes include lactic acidosis, ketoacidosis, and uremia. Lactic acidosis can occur when tissue perfusion is impaired or oxygen utilization is disrupted, leading to lactate buildup. Ketoacidosis occurs when ketones build up, often in states of insulin deficiency or prolonged starvation. Uremia reflects holding back of acids and other waste products when kidney function is severely reduced.
From an interpretation standpoint, a high-gap disorder often produces a reduced bicarbonate level and a reduced pH. The respiratory system may respond by lowering the partial pressure of carbon dioxide through increased ventilation. That compensation can partially blunt acidemia, but it does not remove the underlying metabolic problem. This is why using blood gas analysis alongside the anion gap strengthens diagnostic accuracy.
High-gap metabolic acidosis can also coexist with other acid-base disorders. For example, a patient may have a high-gap process and a simultaneous metabolic https://anion-gap-calculation.com/calculators/strong-ion-difference.html alkalosis or respiratory disorder. In these cases, the anion gap calculator is a starting point, not the final answer. Careful review of the overall acid-base balance is required to avoid missing a mixed disorder.
Typical Anion Gap Metabolic Acidosis
Metabolic acidosis with a normal anion gap is also called hyperchloremic acidosis. With this pattern, bicarbonate decreases but chloride rises enough to keep the overall gap within the expected reference interval. This finding may still reflect a significant acid-base problem even though the anion gap itself is not elevated.
A frequent mechanism is bicarbonate loss. Base is lost by the body, and chloride increases as a compensatory change. This can occur with gastrointestinal losses such as diarrhea, where bicarbonate-rich fluid is depleted. In the appropriate clinical setting, the combination of low bicarbonate and high chloride points toward this pattern rather than a high-gap disorder.
Another key cause is renal tubular acidosis, in which the kidneys fail to properly acidify urine or reclaim bicarbonate. This leads to a persistent acidotic state despite a normal anion gap. Because the mechanism differs from high-gap acidosis, the treatment approach may also differ. That is why differentiating these entities matters in clinical interpretation.
A normal anion gap acidosis is a good example of why the anion gap calculator should be used together with blood gas analysis. Low pH together with low bicarbonate may indicate metabolic acidosis, but the anion gap tells you whether the problem is due to unmeasured acids or to bicarbonate loss with chloride retention. This distinction is central to the interpretation framework.
Frequent Assessment Errors and Diagnostic Pitfalls
A number of problems can distort the apparent anion gap and cause misinterpretation. One of the most common is laboratory error, which can arise from sample processing, machine variation, or data entry errors. If the result does not fit the patient’s condition, the chemistry should be rechecked before making big decisions.
Low albumin is another common pitfall. Since low albumin lowers the unmeasured anion pool, the anion gap may appear artificially normal. This is one reason albumin-adjusted calculation is so important. Without it, a major acid load can be missed, especially in inpatient or critically ill patients.
Calcium ion levels and other electrolyte shifts can also alter the broader acid-base environment. While they do not directly define the anion gap, they may influence the overall clinical picture and increase confusion if the analysis focuses only on one number. Detailed review of the electrolyte panel helps reduce this risk.
Another major pitfall is relying on the anion gap without considering pH and carbon dioxide. A calculated value may be helpful, but if the patient has a respiratory disorder or mixed acid-base pattern, the final conclusion can be misleading. Good interpretation uses the anion gap calculator as one component of a larger diagnostic tool, not as a replacement for blood gas analysis.
In the end, reference interval differences between laboratories can produce apparent discrepancies. A result that seems slightly elevated in one setting may be normal in another depending on the analyzer, method, and reporting conventions. Understanding the local reference range is essential for sound clinical interpretation.
FAQ About Anion Gap and Blood Gases
How do you calculate the anion gap from blood gas values?
You typically do not calculate the anion gap from the blood gas alone. The anion gap calculator relies on serum sodium, serum chloride, and bicarbonate from the chemistry panel. Blood gas analysis adds pH and partial pressure of carbon dioxide so you can interpret the acid-base disorder more fully. If the blood gas reports a bicarbonate value, it can offer context, but the standard calculated value is still based on serum electrolytes.
What’s the normal anion gap range in adults?
The reference interval depends on the laboratory procedure and whether potassium is included. A number of laboratories report a typical anion gap in the low to mid teens, but the exact range should always be checked against the local report. The most important step is to compare the result with the lab’s own interval rather than using a single cutoff.
Why do you adjust the anion gap for albumin?
Albumin correction is required because blood albumin is a major unmeasured anion. If albumin levels are low, the anion gap may appear incorrectly normal even when an acid burden is present. The albumin-corrected anion gap improves detection of occult acidosis and provides a better estimate of the underlying metabolic state.
Is blood gas analysis alone enough to show metabolic acidosis?
Blood gas analysis can strongly indicate metabolic acidosis by demonstrating a low pH and low bicarbonate, but it does not always explain the cause. The anion gap helps separate between high anion gap metabolic acidosis and normal anion gap metabolic acidosis. Considering both together provides a better interpretation framework than blood gas alone.
What leads to a high anion gap in clinical interpretation?
Typical sources include lactic acidosis, ketone-related acidosis, and uremia. Such conditions cause a higher anion gap by introducing undetected acids to the bloodstream. If the anion gap is high, the result should be read alongside pH, bicarbonate, and carbon dioxide so you can judge the severity of the acid-base disturbance and whether respiratory compensation is present.